Developmental Frame of Reference in Occupational Therapy
The developmental frame of reference: Llorens' premises, Mosey's adaptive skills, interventions, worked cases, comparisons with other frames, and a quiz.


The developmental frame of reference is based on typical human development. Occupational therapists generally use it with children who have gross motor or fine motor delays. Developmental theories describe patterns or sequences of development that are accepted as typical for children.
The theories and concepts behind the developmental frame of reference come from many experts. Lela Llorens was one of them, and she described the developmental frame of reference for occupational therapy.
According to Llorens, occupational therapy is a facilitation process that assists the individual in achieving mastery of life tasks and the ability to cope as efficiently as possible with the life expectations made of him or her, through the mechanism of selected input stimuli and the availability of practice in a suitable environment.
In the clinical setting, this theory is applied when the occupational therapist facilitates, or assists, the client’s adaptation process within their environment.
It helps to understand the basic terminology of a frame of reference before reading about a specific one. If you’re not familiar with it, read our guide to occupational therapy frames of reference first.
Theoretical base
The developmental frame of reference draws on classic developmental theories. Llorens charted development across many domains and life stages, bringing together the work of theorists such as Erikson (psychosocial), Piaget (cognitive) and Gesell (motor and maturational). Two of these theories are summarised below.
- 0–1½ years
- Erikson: trust vs mistrust
- Piaget: sensorimotor stage (0–2)
- 1½–3 years
- Erikson: autonomy vs shame and doubt
- Piaget: preoperational stage begins (2–7)
- 3–5 years
- Erikson: initiative vs guilt
- 5–12 years
- Erikson: industry vs inferiority
- Piaget: concrete operational stage (7–11)
- 12–18 years
- Erikson: identity vs role confusion
- Piaget: formal operational stage (12+)
- Adulthood
- Erikson: intimacy vs isolation, generativity vs stagnation
- Older age: integrity vs despair
Age ranges are approximate and vary between textbooks.
Function–dysfunction continua: Llorens’ 10 premises
Llorens constructed 10 premises that fit together in a sequence to support her vision of growth and development (Llorens, 1970).
| # | Premise (in simple words) |
|---|---|
| 1 | People develop horizontally in neurophysiological, physical, psychosocial and psychodynamic growth, and in social language, daily living and sociocultural skills, at specific periods of time. |
| 2 | People develop longitudinally in each of these areas in a continuous process as they age. |
| 3 | Mastering the skills, abilities and relationships in each area, both horizontally and longitudinally, is necessary for satisfactory coping and adaptive relationships. |
| 4 | This mastery is usually achieved naturally in the course of development. |
| 5 | A person's natural endowment and the experiences received within the family interact to promote positive early growth in both planes. |
| 6 | Later, extended family, community and social groups support the growth process. |
| 7 | Physical or psychological trauma from disease, injury, environmental insufficiency or personal vulnerability can interrupt growth and development. |
| 8 | Such a growth interruption causes a gap in the developmental cycle: a difference between expected coping and adaptation and the skills needed to achieve them. |
| 9 | Occupational therapy, through the skilled use of activities and relationships, can provide growth links that close the gap between expectation and ability. |
| 10 | Occupational therapy, through the skilled use of activities and relationships, can provide growth experiences that prevent maladaptation related to insufficient nurturance. |
Evaluation: behaviours indicative of function and dysfunction
When applying the developmental frame of reference, the OT assesses the client’s current level of skills at stage-specific periods across all domains.
Growth happens in many areas at the same time. The OT looks at the child as a whole, so it’s important to assess the development of all skills at a specific period, and to identify gaps in the developmental pattern and milestones. For example, the OT assesses a child’s fine motor skills, gross motor skills, social skills, language and other areas at the same time.
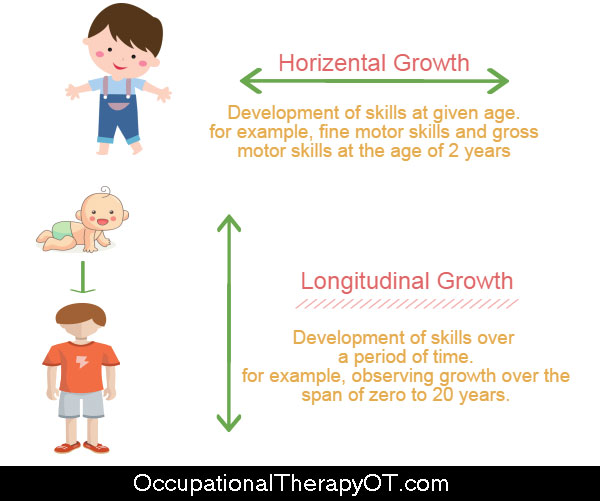
The interweaving of each area supports the child’s future growth. Llorens’ terms horizontal and longitudinal can be confusing, so she later clarified them:
| Horizontal development | Longitudinal development | |
|---|---|---|
| Concept | Simultaneous: gains in all areas that appear at a given age | Chronological: growth in one area over time |
| Question it answers | What can a 3-year-old do across every area? | How does hand use change from birth to 20 years? |
| Example | At 3: strings large beads, puts on some clothes, uses a fork, talks in back-and-forth conversation, joins other children to play | Palmar grasp in infancy, then a fisted crayon grip, then a mature pencil grasp, then fluent handwriting and typing |
3-year-old examples from CDC, Learn the Signs. Act Early. (2022).
Common developmental assessments include the Peabody Developmental Motor Scales (PDMS-2), the Bayley Scales of Infant and Toddler Development, the Hawaii Early Learning Profile (HELP), the Denver II screening test and the Bruininks-Oseretsky Test of Motor Proficiency (BOT-2), along with observation of play, self-care and family routines.
Postulates regarding change and intervention
In this phase, the OT plans the objectives and goals for the child. After assessment, the OT may find a disruption in the typical progression of growth and development, due to illness, injury, a genetic or chromosomal condition, or a lack of opportunity.
Postulates regarding change focus particularly on the gaps in the developmental cycle. A growth interruption may cause a wide variety of problems for the child and their ability to interact with the environment.
We believe that what is commonly called the “developmental frame of reference” is truly a frame of reference in which the therapist uses various contemporary, legitimate tools of the profession to facilitate the traditionally accepted sequence of typical development. This involves:
- the therapist’s clinical reasoning
- adapting the environment
- teaching and learning theories
- additional growth-enhancing experiences
- the conscious use of self
In these situations, the therapist identifies the critical skills the child needs within the accepted developmental sequence, and uses these tools and external factors to help the child develop those skills.
-
Assess every domain
Find the child's current level in motor, sensory, cognitive, language, social and self-care skills.
-
Find the gap
Compare with age expectations and with what the child and family need day to day.
-
Pick the next step
Choose the skill that comes next in the sequence, not the skill expected for the child's age.
-
Practise through play
Activities just above the current level, in a supportive environment, repeated often.
-
Re-assess and move on
When a skill is mastered, move to the next one in the sequence.
A case example
Kabir is 4 years old and was born at 30 weeks. His parents say he avoids drawing and gets frustrated with buttons. On assessment, his fine motor skills are closer to a 2½–3-year level: he holds a crayon in his fist and can copy a vertical line but not a circle. His language and social skills are on track for his age.
| Current level | Next step in the sequence | Activities |
|---|---|---|
| Fisted crayon grip | Fingers-and-thumb grip | Short, broken crayons and chalk, which encourage a finger grip; drawing on a vertical easel |
| Copies a vertical line | Copies a circle, then a cross | Drawing roads for toy cars, tracing circles in sand and shaving foam |
| Pulls off loose clothes | Unbuttons large buttons | Button boards with big buttons, dressing-up play, posting coins in a slot |
Strengths and limitations
| Strengths | Limitations |
|---|---|
| Gives a clear, logical order for setting goals | Development doesn't always follow a fixed sequence; children vary widely |
| Looks at the whole child across all domains | Can focus on milestones more than on what matters to the family |
| Fits well with standardised developmental tests | Some children, e.g. with severe physical disability, may need compensation rather than following the typical sequence |
Mosey’s developmental frame for adults: recapitulation of ontogenesis
The developmental idea isn’t only for children. In psychosocial OT, Anne Cronin Mosey described recapitulation of ontogenesis: adults with mental illness may not have fully developed certain adaptive skills, and therapy recreates the conditions for each next stage.
| Adaptive skill | What it involves |
|---|---|
| Perceptual-motor | Integrating sensory information and movement |
| Cognitive | Thinking, problem solving and planning |
| Drive-object | Directing energy towards goals and objects |
| Dyadic interaction | One-to-one relationships |
| Group interaction | Participating in groups, from parallel to mature groups |
| Self-identity | A sense of self as worthy and capable |
| Sexual identity | Accepting one's sexuality and related roles |
Mosey's developmental group levels (parallel, project, egocentric-cooperative, cooperative, mature) come from the group interaction skill. See OT in mental health.
More worked examples
| Client | Current level | Next step and activity |
|---|---|---|
| Mia, 18 months, Down syndrome | Sits with support | Independent sitting: play while sitting on a parent's lap, then on the floor with cushions |
| Leo, 5, DCD | Copies a cross but not a square | Square copying: drawing 'boxes' for toy cars, tracing in sand |
| Ravi, 28, schizophrenia | Parallel group level | Project group: a short shared poster activity |
Developmental vs related frames
| Developmental | Acquisitional | Neurodevelopmental (NDT) | |
|---|---|---|---|
| Focus | Typical developmental sequence | The specific skill needed now | Posture and movement quality after CNS damage |
| Starting point | Current developmental level | The functional task | Movement analysis |
| Example | Fine motor stages before handwriting | Teach shoelace tying directly | Handling to support sitting balance |
Read the acquisitional and NDT guides.
Test yourself: developmental frame
0 / 3 correct
-
Llorens' 'horizontal' development refers to…
Show answer
B. Horizontal development means gains in all domains at a given age; longitudinal means growth over time.
-
Which is one of Mosey's adaptive skills?
Show answer
B. Dyadic interaction (one-to-one relationships) is one of Mosey's adaptive skills.
-
In the developmental frame, therapy targets…
Show answer
B. Therapy works just above the current level in the typical sequence.
Summary
The developmental frame of reference uses the typical sequence of development to understand where a person is and where they need to go next. Following Llorens, the occupational therapist looks at development horizontally and longitudinally, finds the gaps left by growth interruptions, and uses activities and relationships to close them. Read more:
- Occupational therapy frames of reference
- Biomechanical frame of reference
- Model of Human Occupation (MOHO)
- Rehabilitative frame of reference
- Psychodynamic frame of reference
References
- Llorens LA. Facilitating growth and development: the promise of occupational therapy. American Journal of Occupational Therapy. 1970;24(2):93–101.
- Kramer P, Hinojosa J, Howe TH, eds. Frames of Reference for Pediatric Occupational Therapy. Wolters Kluwer.
- Pendleton HM, Schultz-Krohn W, eds. Pedretti’s Occupational Therapy: Practice Skills for Physical Dysfunction. Elsevier.
- Boyt Schell BA, Gillen G, eds. Willard and Spackman’s Occupational Therapy. Wolters Kluwer.
- Centers for Disease Control and Prevention. CDC’s developmental milestones.
- Mosey AC. Three Frames of Reference for Mental Health. SLACK; 1970.
- Mosey AC. Psychosocial Components of Occupational Therapy. Raven Press; 1986.
Frequently asked questions
What is the developmental frame of reference in occupational therapy?
Who developed the developmental frame of reference?
What is horizontal and longitudinal development?
When is the developmental frame of reference used?
What assessments are used in the developmental frame of reference?
What are the principles of the developmental frame of reference?
What are Mosey's adaptive skills?
What are interventions in the developmental frame of reference?
Written by
Deepam Pawar, OT
Deepam Pawar is an occupational therapist and co-founder of Occupational Therapy OT. He focuses on clinical frameworks, assessment, and evidence-based practice.
All articles by Deepam →This article is for general education and is not a substitute for individualized assessment or treatment by a licensed occupational therapist. Always seek the guidance of a qualified professional for specific concerns.





