Occupational Therapy for Down Syndrome: Early Intervention, Activities and Tips
How OT helps children with Down syndrome: milestones, early intervention, feeding, motor and daily-living skills, activities, safety tips and advice for parents.


What is Down syndrome?
Down syndrome is a genetic condition caused when abnormal cell division results in extra genetic material from chromosome 21. It is a naturally occurring chromosomal arrangement that has always been part of the human condition, present across all races, genders and socio-economic groups. Each year, about 5,775 babies in the US are born with Down syndrome (CDC). It is present at birth and affects the body’s physical and mental development.
Normally, a child inherits two copies of chromosome 21, one from each parent. If a child has an extra chromosome 21, they will have Down syndrome. Because Down syndrome usually affects every cell in the body, people can have a variety of medical needs, such as heart conditions, hearing and vision problems and thyroid differences, which doctors monitor regularly.

| Type | What happens | How common |
|---|---|---|
| Trisomy 21 | Every cell has three copies of chromosome 21 | About 95% |
| Translocation | Part of chromosome 21 is attached to another chromosome | About 4% |
| Mosaic | Only some cells have the extra chromosome 21 | About 1% |
Approximate figures from the National Down Syndrome Society.
Common features
No two people with Down syndrome are exactly alike, but they share some common physical features. Babies with Down syndrome often have similar facial features, lower muscle tone, and usually learn to walk and talk later than other children. Common features include:
- A slightly small head that is flattened at the back
- Up-slanted eyes, with extra skin folds at the inner corners
- Small ears, nose and mouth
- Short stature
- Small hands and feet
- Some degree of intellectual disability, which varies widely
How Down syndrome is diagnosed
Professional guidelines (ACOG) recommend that every pregnant person is offered screening and the option of diagnostic testing, regardless of age.
- Screening tests estimate the chance that a baby has Down syndrome but cannot confirm it. They include cell-free DNA screening from a blood sample, first-trimester screening (ultrasound plus a blood test), second-trimester blood screening (the “quad screen”) and ultrasound.
- Diagnostic tests confirm the diagnosis using cells from the pregnancy. Chorionic villus sampling (CVS) takes a sample from the placenta, usually at 10–13 weeks. Amniocentesis takes fetal cells from the amniotic fluid, usually after 15 weeks.
- After birth, the diagnosis is confirmed with a chromosome test (karyotype) from a blood sample.
Down syndrome and development
Children with Down syndrome want to do what all children want to do: sit, crawl, walk, explore their environment and interact with the people around them. To do that, they need to develop their gross motor skills.
Because of certain physical characteristics, including hypotonia (low muscle tone), ligamentous laxity (loose ligaments that make the joints very flexible) and decreased strength, children with Down syndrome don’t develop motor skills in the same way as typically developing children. Infants with Down syndrome usually have central hypotonia, and as a result gross motor skills are delayed. Many children with Down syndrome do not sit up until about 1 year or walk until about 2 years (Melyn and White, 1973).
| Milestone | Range for Down syndrome | Typical range |
|---|---|---|
| Responsive smile | 1–5 months | 1–3 months |
| Sits alone | 6–36 months | 5–9 months |
| Crawls | 8–22 months | 6–12 months |
| Stands | 1–3¼ years | 8–17 months |
| Walks alone | 1–4 years | 9–18 months |
| Finger feeds | 10–24 months | 7–15 months |
| Drinks from a cup unassisted | 12–32 months | 9–18 months |
| Uses a spoon | 13–39 months | 12–20 months |
| First word | 1–4 years | 1–2 years |
| Two-word phrases | 2–7½ years | 15–32 months |
| Bowel control | 2–7 years | 16–42 months |
| Dresses self unassisted | 3½–8½ years | 3¼–5 years |
Source: National Down Syndrome Society. The ranges are wide; every child develops at their own pace.
The goal of occupational therapy for these children is not to speed up their development, as is often assumed, but to help them develop the best possible movement patterns. Over the long term, therapists want to help the child develop good posture, proper foot alignment, an efficient walking pattern, and a strong physical foundation for fine motor skills and activities of daily living.
Early intervention for Down syndrome
Early intervention is a systematic program of therapy, exercises and activities designed to address the developmental delays children with Down syndrome may experience. Its goal is to enhance the development of infants and toddlers and to help families understand and meet their child’s needs. The most common early intervention services for babies with Down syndrome are physical therapy, speech and language therapy, and occupational therapy. Read more about early intervention in OT.
| Therapy | Main focus in the early years |
|---|---|
| Physical therapy | Gross motor skills: head control, sitting, crawling, standing and walking, with good posture, foot alignment and an efficient walking pattern |
| Occupational therapy | Feeding and oral-motor skills, positioning, arm and hand movements that lay the foundation for fine motor skills, sensory processing, play and later self-care |
| Speech and language therapy | Communication from the start: understanding, early sounds, signing and pictures, then speech |
When your child is an infant, your immediate concerns are about their health and growth, the basic motor milestones, social interaction with you and others, their interest in what’s going on around them, and early speech sounds and responses. At this stage an OT may become involved to:
- Help with oral-motor feeding problems (also addressed by speech-language pathologists). Because of low tone and weakness in the cheeks, tongue and lips, feeding is difficult for some infants with Down syndrome. OTs suggest positioning and feeding techniques, and can be involved in feeding studies if needed.
- Help with motor milestones, particularly fine motor skills. OTs and physical therapists work closely together on the gross motor milestones of sitting, crawling, standing and walking. The OT also promotes arm and hand movements that lay the foundation for later fine motor skills. Low muscle tone and loose joints are real challenges to early motor development, and OT helps the child meet them.
Communication
Most children with Down syndrome learn to speak and use speech as their main way of communicating. They understand language and want to communicate well before they can speak. Total communication, using sign language and pictures, can serve as a transitional communication system. Parents are a baby’s main communication partners, so parents can do a great deal to help their child learn to communicate; many pre-speech and pre-language skills are best learned at home.
Occupational therapy assessment for Down syndrome
A child with Down syndrome may have delays in gross motor skills, fine motor skills, thinking skills and communication. The OT assesses all areas of development (gross motor skills, fine motor skills, behaviour, social skills, cognition and perception) for comprehensive planning, using formal and informal tests.
| Area | What the OT checks |
|---|---|
| Sensorimotor | Muscle tone, strength and endurance; range of motion; coordination and balance; posture; hand function |
| Cognitive and perceptual | Attention, memory, figure-ground perception (picking out an object from a busy background), directionality |
| Social | Social smile, peer relationships, group interaction |
| Behaviour and communication | Tantrums, and verbal and non-verbal communication |
| Daily living | Feeding, dressing, toileting and other self-care |
Occupational therapy intervention for Down syndrome
The occupational therapist plans intervention strategies around each child’s specific needs, using functional, play-based activities. OT provides early intervention to infants and toddlers with Down syndrome, and continues through the school years.
Neurodevelopmental therapy (NDT)
NDT looks at the child’s sensorimotor skills. NDT combined with functional activities works best for children with Down syndrome. If a child is behind on early milestones, the OT focuses on:
- Proper handling techniques
- Facilitating active movement and inhibiting unwanted movement
- Improving reach and grasp for functional play
- Weight-bearing and weight-shifting techniques
- Positioning and adaptive equipment
Sensory integration
Children with Down syndrome may have sensory differences in touch, body position, movement and balance. The occupational therapist uses the principles of sensory integration to help. This approach helps the child regulate their arousal level and improves their ability to attend to a task. Activities may include:
- Balance activities such as bouncing and swinging
- Tactile activities such as massage and play dough
- Oral-motor activities such as blowing, drinking from a straw and chewing
Behavioural strategies
Some children with Down syndrome refuse certain activities or have tantrums, often when a task feels too hard or they can’t yet say what they want. Behavioural strategies such as praise, rewards and clear routines reduce these difficulties, and visual supports and signing help the child communicate instead.
Activities of daily living (ADL)
Children with Down syndrome may need extra time and practice to learn daily-living skills, and may depend on parents for routine tasks. The occupational therapist works to make them as independent as possible. An ADL board, with buttons, zips, buckles and laces, can help teach these skills step by step.
Occupational therapy activities for children with Down syndrome
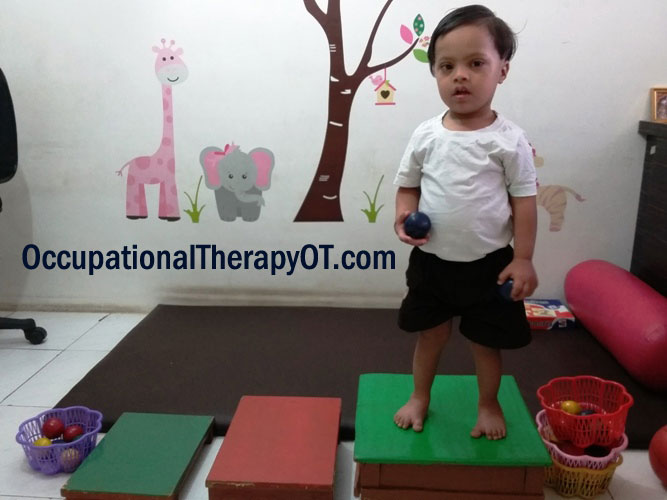
| Skill area | Activities |
|---|---|
| Gross motor and balance | Walking on a balance beam with or without support; obstacle courses; balance board games such as clapping up and down, front and back (for laterality and direction); catching and throwing a ball on the balance board; jumping on a trampoline (with medical clearance) |
| Strength and core | Wheelbarrow walking to strengthen the arms; reaching across the body to grab an object while on a bolster swing (crossing the midline, reaching and core activation) |
| Coordination | Climbing a static or dynamic ladder for eye-hand and hand-leg coordination |
| Hand strength | Theraband push-pull activities; therapy putty; elastic bands; dynamic sand |
| Fine motor control | Pegboard activities; tongs for pre-scissor skills; paper cutting and pasting |
| Daily living | ADL board practice; spoon and cup drinking; pulling on loose clothes; toothbrushing with a mirror |
Tips for parents of a child with Down syndrome
Down syndrome has no cure, but the medical conditions associated with it can be treated and managed, and support is specific to each person’s needs. That’s why it is so important for parents to understand the basics of good parenting for a child with extra needs. Here are a few important tips.
- Accept the reality. Your child has a disability. It might be physical, learning or something else. But having a disability doesn’t make your child a burden to society. Acceptance lets you take clear, positive action. Never hide it; it is never an embarrassment or a curse. Keep a high level of patience, conviction and commitment: raising a child is an ongoing process of many years, so enjoy every bit of it. Listen to everyone and try things, but make your own decisions.
- Teach your child to love and be loved. Children are innocent and need pure love. If you don’t show your child love, they won’t learn to love themselves. Spend quality time together.
- Be positive. Actors such as Chris Burke, Tommy Jessop and Lauren Potter have shown what people with Down syndrome can achieve. Children with Down syndrome are part of this world and can do so much; they just need support from their families.
- Involve them actively. Include your child in daily routine tasks. Help them at first and give cues if needed, then step back.
- Identify their talents and nurture them. Never push your own wishes on your child. Encourage their strengths, and don’t try to control their destiny. Be their friend, guide and facilitator. Every child has talents; finding them can be hard, but it is worth it.
- Look after yourself too. Children pick up on their parents’ stress. Find support through parent groups, family, friends and respite care, so you have the energy your child needs. No one will be as focused on your child’s welfare as you are.
- Last but not least: never give up.
Growing up with Down syndrome
Support continues through school and beyond. In school, OTs help with handwriting, scissors, keyboarding, organisation and self-care, often as part of an IEP. As teenagers and adults, many people with Down syndrome learn to cook, travel, manage money, work and live with varying levels of independence. Occupational therapists support each of these steps.
Related guides: Oral motor activities for toddlers.
References
- Centers for Disease Control and Prevention. About Down syndrome.
- National Down Syndrome Society. Early intervention.
- American College of Obstetricians and Gynecologists. Screening for fetal chromosomal abnormalities. Practice Bulletin No. 226. Obstetrics and Gynecology. 2020.
- Melyn MA, White DT. Mental and developmental milestones of noninstitutionalized Down’s syndrome children. Pediatrics. 1973;52(4):542–545.
- Batshaw ML, ed. Children with Disabilities. 4th ed. Paul H. Brookes.
- Bruni M. Fine Motor Skills for Children with Down Syndrome: A Guide for Parents and Professionals. 3rd ed. Woodbine House; 2016.
- Winders PC. Gross Motor Skills for Children with Down Syndrome: A Guide for Parents and Professionals. 2nd ed. Woodbine House; 2013.
Frequently asked questions
How does occupational therapy help a child with Down syndrome?
When should a baby with Down syndrome start occupational therapy?
When do children with Down syndrome sit, crawl and walk?
What is the difference between physical therapy and occupational therapy for Down syndrome?
What activities help a child with Down syndrome at home?
Can children with Down syndrome become independent?
Written by
Payal Mehta, OT
Payal Mehta is a practising occupational therapist and co-founder of Occupational Therapy OT. She writes on pediatrics, sensory integration, and mental-health practice.
All articles by Payal →This article is for general education and is not a substitute for individualized assessment or treatment by a licensed occupational therapist. Always seek the guidance of a qualified professional for specific concerns.


